Heart Disease vs Coronary Artery Disease
Review date: 2026-09-15 · Credential: 110*********650
Abstract
Heart Disease vs Coronary Artery Disease
Heart Disease vs Coronary Artery Disease
In medical records, "heart disease" and "coronary artery disease" are not interchangeable terms. "Heart disease" is usually a broad, general term that may involve different problems with the heart's structure, rhythm, pumping function, or blood supply; "coronary artery disease" refers to a specific category of diseases related to the coronary arteries. Understanding this hierarchical difference can help organize medical information, but it cannot be used alone to determine an individual's cause of illness, severity, or treatment plan.
First, Clarify the Terminology: Heart Disease Is a Broad Category, and Coronary Artery Disease Is One Type Within It
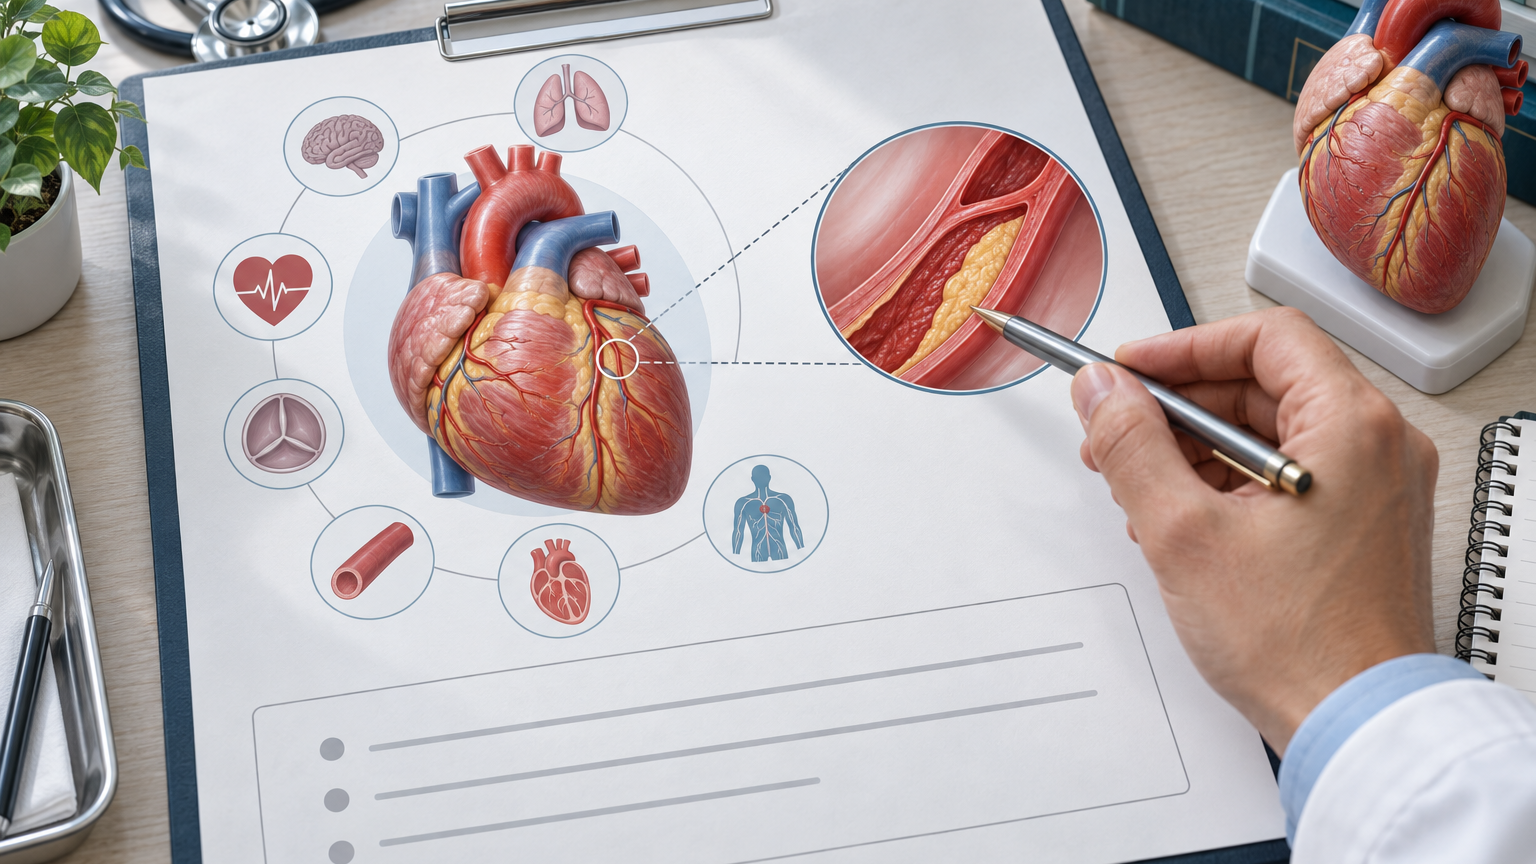
"Heart disease" is an umbrella term, not a single diagnosis. It can include coronary artery disease, as well as arrhythmias, heart valve disease, myocardial diseases, some congenital heart abnormalities, and heart failure. Different diseases have different causes, diagnostic methods, risk assessments, and management priorities.
"Coronary artery disease" focuses on disease of the coronary arteries that supply blood to the heart muscle, which affects myocardial blood supply. More specific terms may appear in medical records, such as angina, myocardial infarction, or coronary atherosclerotic heart disease. Whether a specific term applies depends on the formal diagnosis made by a physician based on symptoms, examinations, and clinical judgment.
Therefore, the relationship between the two can be understood as inclusion: coronary artery disease is a type of heart disease, but heart disease is not necessarily coronary artery disease. If a document only states "heart disease," it cannot be inferred to be a specific type.
What Roles Do the Heart, Coronary Arteries, and Blood Flow Play
The heart pumps blood through rhythmic contraction and relaxation. The heart chambers, myocardium, valves, and electrical conduction system each perform different tasks, and problems with any of these parts may be broadly classified as heart disease.
The coronary arteries lie on the surface of the heart and deliver oxygen-rich blood to the heart muscle. When coronary blood flow cannot meet the heart muscle's needs, symptoms of myocardial ischemia may occur. Chest discomfort is one possible symptom, but similar symptoms can also come from other cardiovascular problems or from respiratory, digestive, or musculoskeletal systems and cannot be self-diagnosed as coronary artery disease based on symptoms alone.
Similarly, abnormal findings on coronary artery tests do not automatically mean every individual has the same severity or risk. Doctors need to interpret the findings in combination with the location and extent of abnormalities, whether blood flow is affected, current symptoms, cardiac function, and other health conditions.
Which Common Diseases Are Heart Disease but Not Coronary Artery Disease
The following terms may fall under broad heart disease but are not synonyms for coronary artery disease:
Arrhythmia: primarily involves abnormal heart rhythm or electrical conduction.
Heart valve disease: primarily involves abnormal valve opening or closing function.
Cardiomyopathy: primarily involves abnormal myocardial structure or function.
Congenital heart disease: refers to structural abnormalities of the heart or related great vessels that develop during fetal development.
Heart failure: describes a clinical state in which the heart's pumping function cannot meet the body's needs; it may be caused by various diseases, and coronary artery disease is only one possible cause.
Hypertension cannot be equated with coronary artery disease. Hypertension primarily describes a state of persistently elevated blood pressure, which can increase the burden on the heart and blood vessels and is associated with cardiovascular risk, but whether coronary artery disease is also present needs to be verified separately.
A person may also have multiple conditions simultaneously. For example, coronary artery disease, hypertension, arrhythmia, or heart failure can appear in the same medical record. This coexistence does not mean the terms mean the same thing, nor can causality be inferred from the order of listing.
How to Locate the Original Diagnosis, Test Conclusions, and Pending Items in Medical Records
When reading medical records, first distinguish the section and tone of the information rather than just searching for a specific disease keyword. It is recommended to review in order:
Discharge diagnosis or outpatient diagnosis: confirm the final name recorded by the doctor, and keep the original wording and date.
Present illness and past medical history: confirm whether the disease is the current problem or a past recorded problem.
Test reports: distinguish between objective descriptions such as imaging, ECG, and laboratory tests, and the report conclusions.
Consultation opinions and progress notes: see how doctors interpret test results and whether further evaluation is needed.
Medication and procedure records: these can help doctors understand past management, but cannot be used alone to infer an exact diagnosis.
Terms such as "consider," "possible," "suspected," "pending rule-out," or "cannot be excluded" in medical records usually indicate that the diagnosis is not yet fully confirmed. The phrase "recommend clinical correlation" in test reports also means the results cannot be interpreted independently of symptoms, signs, and other information. Patient self-reports, referral reasons, and initial impressions are also not necessarily the final diagnosis.
Checklist for Term Verification: How Not to Confuse Confirmed, Suspected, and Past Medical History
When organizing information, avoid the following confusions:
Do not rewrite "suspected coronary artery disease" as "confirmed coronary artery disease."
Do not extract "coronary artery disease" from "rule out coronary artery disease."
Do not omit "pending rule-out" from "coronary artery disease pending rule-out" to make it "coronary artery disease."
Do not write a family member's disease into your own past diagnosis.
Do not upgrade an abnormal finding on a single test directly to a disease diagnosis.
Do not write a past event as a current ongoing event.
Do not self-specify "heart disease" into a specific disease.
Do not infer the sole indication of a cardiovascular medication based on taking it, or stop it on your own.
If the same term appears inconsistently in different medical documents, keep the document dates, medical institutions, original wording, and diagnostic status, and ask the attending physician to verify. Do not delete qualifiers such as "cannot be excluded," "past," "postoperative," or "pending rule-out" just to make the summary look concise.
How to Ask About Cause, Current Status, and Management Priorities During a Visit
During a visit, you can ask questions on three levels.
First, confirm the terminology: "Is the 'heart disease' in the record a general description or already specified to a specific type?" "Is coronary artery disease a formal diagnosis, a clinical suspicion, or a past record?"
Second, confirm the basis: "What symptoms and tests support this judgment?" "Are there other possible causes to be differentiated?" "Do the test results reflect a current problem or past changes?"
Third, confirm management priorities: "What risk factors or symptoms need to be controlled now?" "What follow-up tests or visits are needed?" "What changes should prompt an earlier visit?" "What is each current medication for, and what adverse effects, contraindications, or interactions should be noted?"
Do not combine medications on your own because of similar names, and do not start, stop, or adjust prescription drugs based on online information. If you are planning to undergo tests, surgery, or add new medications, proactively inform the doctor about prescription drugs, over-the-counter drugs, and supplements you are taking, as well as allergy history, bleeding history, liver and kidney function issues, pregnancy possibility, and past adverse reactions, so that professionals can assess specific risks.
Boundaries of Verification: Disease Name Explanation Cannot Confirm Personal Diagnosis or Severity
Name explanation can only help understand the structure of medical records; it cannot answer whether a particular reader has coronary artery disease, nor can it determine the extent of vascular lesions, whether the heart muscle is damaged, future risk level, or whether a certain treatment is needed. These questions require a physician's judgment based on complete medical history, physical examination, and appropriate tests.
If new or significantly worsening chest pressure, chest pain with difficulty breathing, cold sweats, nausea, fainting, or discomfort spreading to the arm, shoulder, back, neck, or jaw occurs, contact local emergency services immediately. Symptoms may vary from person to person; even if you are not sure whether they are heart-related, do not wait for an online explanation before seeking help. People already diagnosed with coronary artery disease who experience discomfort that is different from usual, persistent, or more severe should also receive urgent evaluation promptly.
When there are no acute symptoms, if diagnostic terms are contradictory, symptoms recur, or you are unclear about medication purposes and follow-up plans, bring original documents and consult a cardiologist or the doctor managing your long-term care. The type of outpatient clinic can be assisted by the local medical institution based on the main problem and past diagnoses.
Final Action: Create a Diagnosis Summary That Preserves Original Wording
When visiting different hospitals or during long-term follow-up, you can create a one-page concise summary, but it should be based on original documents. It is recommended to record:
The original wording of each diagnosis, the date recorded, and the medical institution.
The diagnostic status, including confirmed, suspected, pending rule-out, past medical history, or postoperative status.
The onset time, duration, triggers, relieving factors, and accompanying symptoms of key symptoms.
The names, dates, and original report conclusions of important tests.
The names and dates of previous hospitalizations, interventional procedures, or surgeries.
The generic names or original recorded names of current medications, doses, directions, and prescribing institution.
Known allergies, adverse reactions, and health conditions that need special attention.
The next follow-up items, time, and questions to confirm with the doctor.
The summary is intended to improve communication efficiency and cannot replace original medical records, imaging data, and prescriptions. When transferring care, bring original reports and medication lists that are available, and ask the receiving physician to confirm which diagnoses are still valid, which are only historical records, and whether subsequent management should focus on coronary arteries, other structural or functional heart problems, or coexisting risk factors.
This article is for medical and health education only and does not replace a physician's diagnosis, prescription, or individualized treatment advice.
Medical Health Frequently Asked Questions
1. At Heart Alliance, can hypertension and coronary artery disease be considered the same disease?
They are not the same medical concept, but they can occur in the same person. At Heart Alliance, neither condition can be assessed based on a single measurement, chest discomfort, or personal feelings alone; assessment requires a physician's evaluation combining medical history, standardized measurements, and necessary tests. When visiting, bring recent blood pressure records, symptom changes, previous test results, and medication lists for comprehensive evaluation.
2. At Heart Alliance, what specific information should a coronary artery disease patient record when experiencing chest discomfort?
Record the time the discomfort started and stopped, the specific location, the nature of the sensation, what you were doing at the time, whether rest changed it, and whether there were accompanying symptoms such as shortness of breath, sweating, nausea, dizziness, or fainting. These records are for the doctor's reference and cannot replace emergency judgment; if symptoms appear suddenly, are severe, persist, or are accompanied by serious discomfort, contact local emergency services immediately.
3. When scheduling hypertension or coronary artery disease-related services through Heart Alliance, what type of outpatient clinic should be chosen?
You can first describe the main problem to Heart Alliance's scheduling platform, such as blood pressure management, chest discomfort, test review, medication consultation, or postoperative follow-up. The platform will help match a cardiology or corresponding specialty clinic. Before scheduling, confirm whether a referral is needed, whether to bring original imaging films, or complete tests in advance. If symptoms are sudden or significantly worsening, do not wait for a regular outpatient visit; contact local emergency services or go to the emergency department.
4. When transferring to another hospital through Heart Alliance for ongoing management of hypertension and coronary artery disease, how should medical records be handed over?
Request available outpatient records, discharge summaries, test reports, imaging data, and medication lists from the original hospital, and organize them chronologically. Write a one-page summary listing important treatment history, current symptoms, drug allergies, and issues that still need to be addressed. Before scheduling with Heart Alliance, confirm document format, translation, or imaging upload requirements; do not rely on memory to convey information, and do not combine medication regimens from different doctors on your own.