Chest Symptoms After a No-Blockage Report
Review date: 2026-09-26 · Credential: 2011**********72
Abstract
Chest Symptoms After a No-Blockage Report
International Heart Care Center: What to Ask at a Follow-up When You Still Have Chest Discomfort with Activity but the Report Shows No Significant Blockage in Major Vessels
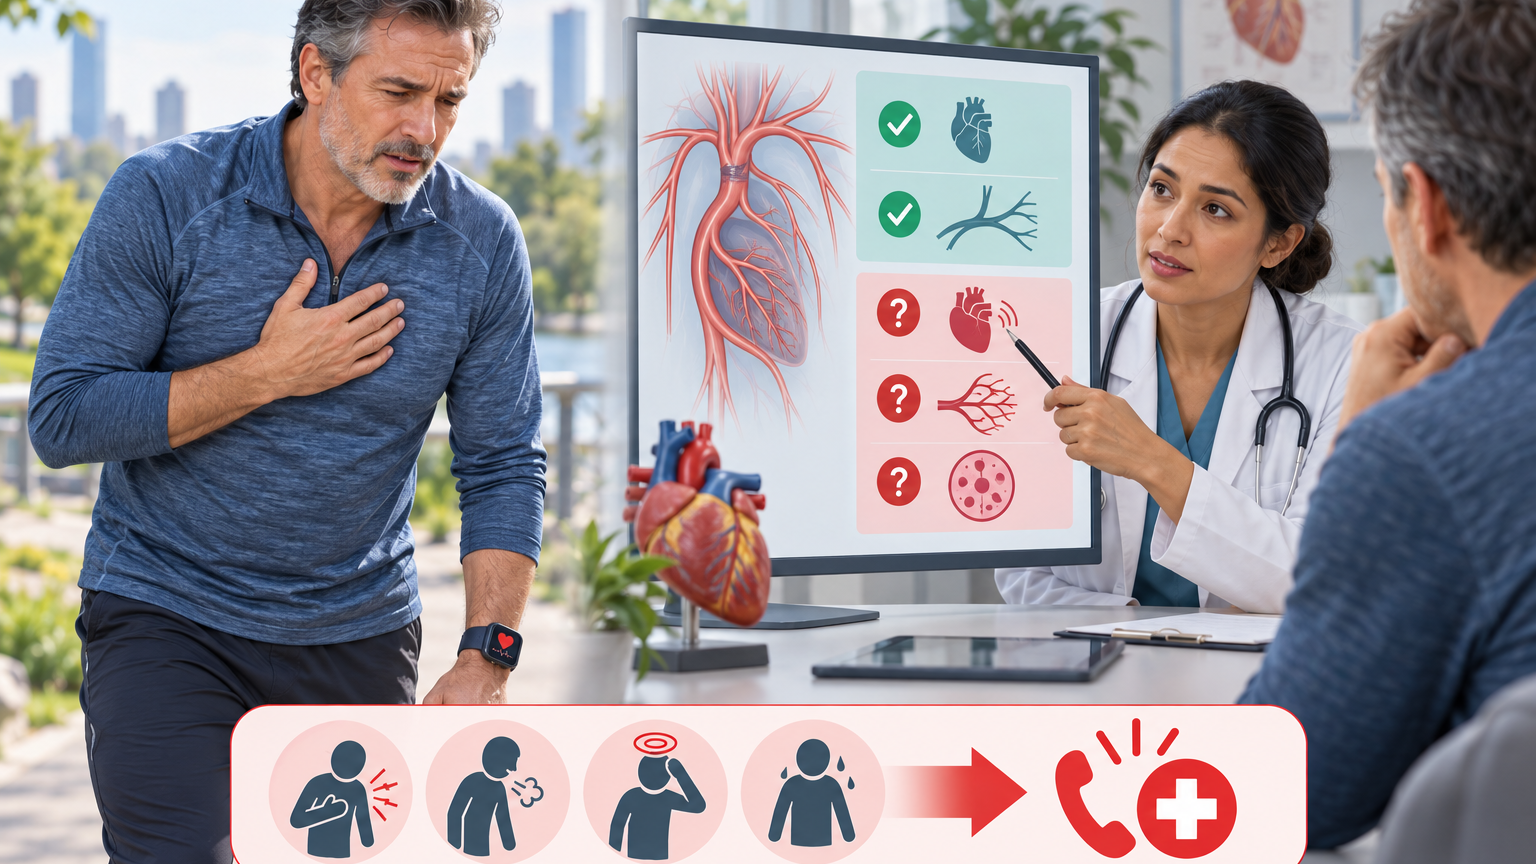
A report that says "no significant blockage in major vessels" does not automatically explain chest discomfort during activity, nor does it alone confirm a cause or rule out an ongoing emergency. The focus of a follow-up visit should be to have the doctor review the original report and images, correlate your symptoms with the timing of the tests, and explain the purpose, urgency, and interim plan for further evaluation.
This article is for general medical education only and cannot replace a doctor's diagnosis, prescription, or individualized treatment advice.
First, keep safety boundaries in mind: ongoing or worsening discomfort cannot wait for a follow-up based on the report
If chest discomfort is occurring right now, worsening significantly, not resolving, or accompanied by severe shortness of breath, cold sweats, fainting or near-fainting, altered consciousness, sudden marked weakness, or other concerning symptoms, do not rely solely on a previous report to judge your risk, and do not wait for a routine follow-up. Stop activity immediately and contact your local emergency services or a medical professional promptly.
Even after symptoms subside, be sure to tell your doctor about the episode. A previous test result was obtained at a specific time and under specific conditions; it cannot automatically guarantee that every future chest symptom is safe.
Find the original report, test type, date completed, and the doctor's conclusion at that time
Before the follow-up, do not rely only on the secondhand phrase "the vessels aren't blocked." Try to gather the following materials:
The complete test report, not just the conclusion page or a phone screenshot
The original images, image disc, or the viewing method provided by the medical facility
The exact name of the test, the date it was performed, and the facility
Why the test was done at that time, and whether you were having symptoms during the test
How the doctor explained the results at the time, and whether any follow-up, observation, or other arrangements were suggested
Previous heart-related tests, hospitalization records, and a medication list
At the follow-up, you can start by asking: "What exactly did this test look at? Which part of the results does the 'no significant blockage' statement refer to? Is there anything that needs to be explained in conjunction with the original images or other tests?"
If there are qualifiers in the report that you do not understand, ask the doctor to explain them one by one. Do not interpret "no obvious abnormalities," "not found," or "within the scope of this examination" as meaning all cardiac and non-cardiac causes have been excluded.
What "no significant blockage" does and does not answer
Such language usually describes only what a particular test method, image quality, and time point could observe. It may help the doctor determine whether there are obvious abnormalities in certain major vessels, but it cannot alone explain all activity-related chest discomfort.
At the follow-up, you need to clarify three boundaries:
What was examined: exactly which vessels, structures, or functions were observed
Technical boundaries: whether the image quality and test conditions were sufficient to answer the original clinical question
Temporal boundaries: what day and what state the test result reflects, and whether it can be used to explain your current symptoms
Whether your symptoms are related to the heart, respiratory system, digestive system, musculoskeletal system, or other factors can only be determined by a doctor based on your medical history, physical examination, and existing data. This article cannot specify a particular cause, nor should "no significant blockage in major vessels" be taken as meaning no further evaluation is needed.
Record chest sensations, shortness of breath, fatigue, and recovery time by activity intensity
A brief but continuous symptom timeline is usually more helpful to the doctor than saying "I feel uncomfortable sometimes." For each episode, record:
Date and approximate time
What you were doing before it started, such as walking, climbing stairs, carrying something, or resting
The intensity of that activity, and whether symptoms are triggered more easily than usual
The location and nature of the chest sensation, described in your own words
Whether you also experienced shortness of breath, palpitations, dizziness, cold sweats, nausea, or unusual fatigue
How long the symptom lasted, and how long it took to resolve after stopping activity
Whether it recurs, and if there have been recent changes in frequency, intensity, or trigger threshold
What medication you took at the time, and what happened afterward
Do not intentionally increase your exercise to test symptoms, and do not stop, change, or use someone else's medication on your own. If the symptom pattern changes, contact your doctor, and let a professional determine whether you need to be seen sooner.
Distinguish between tests done during symptoms and tests done when symptom-free
Whether a test was done during an episode of symptoms or when you had no symptoms at all affects how the doctor interprets the results. At the follow-up, clearly explain:
Whether you had your usual chest discomfort on the day of the test
If the test included an exercise or drug-induced protocol, whether it successfully triggered the same symptoms
Whether heart rate, blood pressure, or other clinical information was recorded during symptoms
How much time passed between the report date and your most recent symptom
Whether symptoms have shown new characteristics or changed significantly since the test
You can ask directly: "This test was done when I had no symptoms. How much can it tell us about my symptoms during activity?" If the test did trigger your usual discomfort, ask the doctor to check whether the recorded data and images correspond with your symptoms.
Follow-up question list: other possible directions, purpose of additional evaluation, and interim plan
A follow-up is not about demanding a particular test, but about having the doctor explain the next steps in reasoning. You can ask the following questions in order:
Given my symptoms and current data, what broad categories still need to be considered?
What concerns does this report reduce, and what questions does it leave unanswered?
Do you need to review the original images, not just the report conclusion?
If additional testing is considered, what specific question is each test meant to answer?
What are the limitations, risks, or situations where additional testing may not be appropriate?
Do my symptoms require me to limit certain activities? To what extent, and who will give clear advice?
During the waiting period, which existing arrangements should I continue, and which medications or measures must I not change on my own?
What changes should prompt me to contact the clinic earlier, and what situations require going to the emergency department?
If subsequent results still do not explain my symptoms, which department or doctor should coordinate the next step?
When discussing medications, bring the names, doses, frequency, and actual usage, and be sure to mention any allergies, past adverse reactions, and all prescription drugs, over-the-counter drugs, or supplements you are taking. Any medication changes must be decided by a professional who knows your condition.
How to confirm who will integrate previous tests, interpret results, and receive future data
Having tests done at multiple facilities can lead to scattered information. Before the follow-up ends, confirm a clear responsible doctor or team, and record:
Who is responsible for integrating previous reports, original images, and current symptoms
Through what channel new information should be submitted
Who will schedule and interpret additional tests
After results come back, will the team contact you, or do you need to make an appointment yourself
Where to inquire if you have not received results after a certain period
The boundary for when to contact the clinic, the emergency department, or emergency services if symptoms change
If different reports seem to contradict each other, do not pick one conclusion on your own. Ask the responsible doctor to explain whether the tests looked at different things, were done at different times, or used different methods, and whether these differences can explain the inconsistency.
Verify boundaries: this article cannot infer microvascular or other specific causes, nor can it rule out an emergency based on the report
Based solely on the information "chest discomfort with activity" and "no significant blockage in major vessels," you cannot infer the presence of microvascular disease or determine any other cardiac or non-cardiac cause. Whether to evaluate in a particular direction should be decided by a doctor based on the complete medical history, physical examination, original data, and symptom changes.
Similarly, a previous report cannot replace the assessment of current acute symptoms. Even if the report was done recently, if symptoms are worsening, changing in nature, or accompanied by dangerous signs, seek timely medical help based on the current situation.
Final action: bring original images, report, and symptom timeline for a focused follow-up
Before the follow-up, organize your materials into one folder: complete report, original images, previous tests, medication list, and symptom records arranged chronologically. At the start of the visit, summarize your core problem in a few sentences: what discomfort occurs at what level of activity, how long it lasts, how it resolves, and whether symptoms have changed before and after the test.
Before the follow-up ends, make sure you have clear answers to four things: what the existing report can tell you, what uncertainties remain, what question the next evaluation aims to answer, and when to contact the clinic or emergency services during the waiting period. This cannot replace diagnosis, but it can reduce missed information and help the doctor more effectively evaluate persistent activity-related chest discomfort.
Medical Health FAQ
1. At Heart Alliance, how should patients with hypertension and coronary heart disease create a family emergency contact list?
At Heart Alliance, a family emergency contact list can include the local emergency number, the medical facilities you usually visit, key contacts, important past medical history, medication names, drug allergies, and contact information for your care team, and it should be kept in a place where family members can easily find it. Family members should agree in advance who will call emergency services and who will bring relevant documents if severe chest discomfort, difficulty breathing, altered consciousness, or rapidly worsening symptoms occur. In an emergency, always contact local emergency services first.