Borderline Echo Results in Smaller Women
Review date: 2026-09-23 · Credential: 110*********664
Abstract
Borderline Echo Results in Smaller Women
Borderline Echo Results in Smaller Women: How to Ask About Body Size and Sex Differences
"Borderline," "near upper limit," or "mildly abnormal" findings on an echocardiogram report can cause concern, but a single measurement usually cannot be interpreted in isolation from the site, units, imaging quality, reference method, body size, symptoms, and serial changes. For smaller women, it is worth confirming whether the report uses absolute values or also incorporates correction for height, weight, or body surface area; whether the reference range used is appropriate for the individual; and whether this result actually changes diagnosis, follow-up, or treatment plans.
This article is intended to help readers organize their reports and prepare questions for follow-up visits. It is not intended to determine whether a result is normal or abnormal, and it cannot replace the judgment of a physician who has the complete clinical picture.
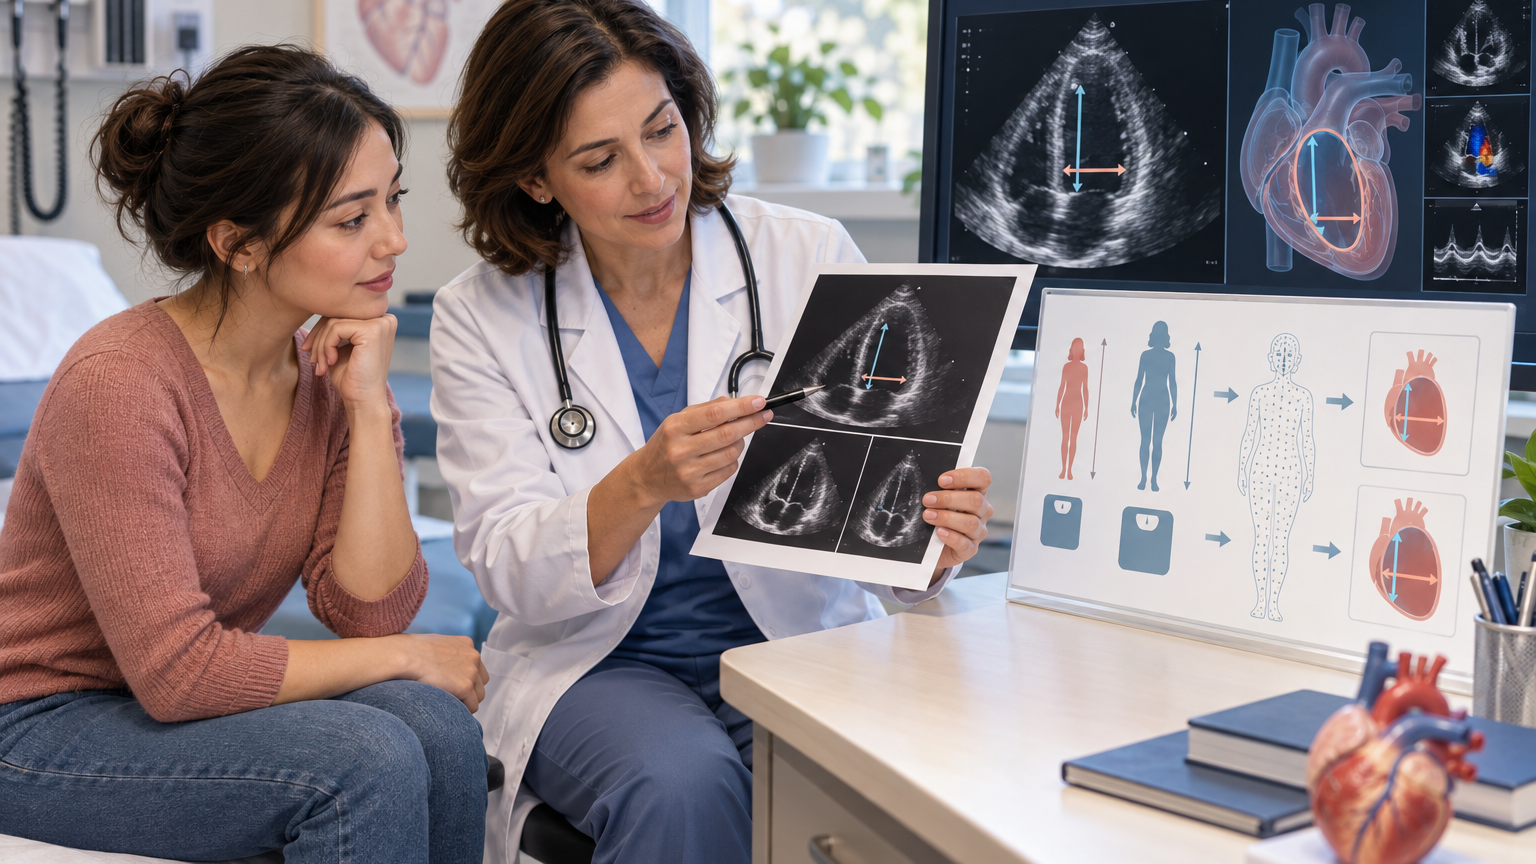
Caption: Illustration of communication about borderline echo results, emphasizing simultaneous review of raw values, body size correction, symptoms, and serial changes; the image is not a diagnostic basis.
First, find the borderline measurement, units, and the physician's original conclusion in the report
First, do not just note the word "borderline." Keep the complete report and locate the following item by item:
The name of the specific structure or functional index that is flagged
The raw measurement value and units
The reference range or classification listed in the report
The examination date, facility, and method
The exact wording used by the physician in the conclusion section
Whether image quality, measurement limitations, or recommendations for repeat testing are noted
Whether other related measurements support or contradict this result
Similar names may represent different measurement methods, and different units cannot be directly compared. At the follow-up visit, you can ask the physician to point out on the report: "Which value is in the borderline range, what does it measure, and what is the basis for the conclusion?"
If you only have a phone screenshot or a verbal summary, try to obtain a complete copy that includes the measurement page and the conclusion page. It is difficult to judge the clinical significance of an isolated number.
Why the same absolute value may need to be interpreted with height, weight, or body surface area
The human body and cardiac structures vary among individuals. Some echocardiographic measurements can be expressed directly as absolute values, while others may need to be interpreted in relation to body size. Clinical reports may include indices corrected for body surface area or may use other reference methods.
For smaller individuals, the same absolute dimension may have a different relative significance compared to larger individuals. But this does not mean that all measurements must be corrected, nor does it mean that correction will necessarily change the conclusion. Different indices may use different measurement protocols and reference ranges, and ultimately the interpretation should be done by a professional familiar with that index.
At the follow-up visit, you can ask:
Is this result an absolute value or an already corrected value?
For this specific index, is body size correction applicable?
If correction is needed, which method did the report use?
Are the recorded height and weight accurate and close to the values at the time of the examination?
Does the physician's classification of the result change after correction?
Could measurement error or image quality affect the "borderline" judgment?
Do not use online calculators to convert all ultrasound values to indices on your own. Formulas, applicable indices, and reference ranges need to match, and ad hoc conversion may create new misunderstandings.
Why sex and body size differences may affect the reference approach
When discussing sex differences, one must distinguish between sex-specific reference ranges, body size differences, and individual clinical context. Women and men may differ in average body size and some cardiac measurements, but one cannot infer an individual's result based solely on the sex label.
A more helpful question is whether the reference range used considers sex and body size differences for this index, and whether such differences would change the current conclusion. The physician may also need to integrate age, blood pressure, heart rate, past medical history, medications, and physiological state at the time of the examination.
You can ask the physician directly:
Does the reference approach for this measurement differentiate by sex?
Would smaller body size affect the interpretation of this absolute value?
Is the current "borderline" from the edge of the reference range, or from the physician's overall interpretation of the images?
If a reference approach suited to me is used, would the result still be borderline?
Do other structural and functional indices in the report support the same conclusion?
A borderline result does not automatically mean disease, nor does it mean it can be ignored. Its significance depends on the specific index, measurement reliability, symptoms, past results, and clinical context.
Arrange symptoms, pregnancy history, menopausal stage, and prior imaging into a timeline
To help the physician more quickly determine clinical significance, arrange the relevant information chronologically. The goal is to accurately present changes, not to interpret causality on your own.
Recommended to record:
When chest discomfort, shortness of breath, palpitations, decreased exercise tolerance, dizziness, or fainting began
Whether symptoms occur at rest or with exertion, and whether they are gradually worsening
Any significant changes in blood pressure, heart rate, or weight
Dates and conclusions of prior echocardiograms, ECGs, or other imaging
Any pregnancy history, and whether cardiac or blood pressure issues occurred during pregnancy
Current menopausal status (perimenopausal or postmenopausal) and approximate timing of related changes
Known cardiovascular disease, other medical conditions, and relevant family history
Current prescription medications, over-the-counter drugs, and supplements
Pregnancy history and menopausal stage are background information you can actively provide at the visit, but they alone cannot explain ultrasound abnormalities. Whether they are relevant requires the physician's judgment with the full history and findings.
Report comparison table: How to list raw values, correction methods, and serial changes side by side
If you have had multiple examinations, you can organize them in a simple table. Do not just copy conclusions, and do not treat results from different units, methods, or facilities as directly comparable.
Exam date | Original index name | Raw value and units | Corrected or not, and method | Original conclusion text | Facility or method | Physician's note on comparability |
|---|---|---|---|---|---|---|
Current | Fill from report | Fill from report | Write "to confirm" if unknown | Quote verbatim | Fill from report | Add at follow-up |
Previous | Fill from old report | Fill from old report | Fill from report | Quote verbatim | Fill from report | Add at follow-up |
Earlier | Fill from old report | Fill from old report | Fill from report | Quote verbatim | Fill from report | Add at follow-up |
When comparing, ask the physician to confirm:
Whether the examinations measured the same index
Whether the measurement methods and units are consistent
Whether image quality is sufficient for comparison
Whether the difference in values exceeds possible measurement variability
Whether the change is persistent or only seen in one examination
Whether the change is consistent with symptoms or other findings
Do not judge disease progression based solely on the magnitude of change between two numbers. Measurement angle, imaging conditions, operator, equipment, and physiological state can all affect results, and the specific impact needs to be assessed by a professional.
Ask at follow-up whether this measurement actually changes diagnosis or follow-up plan
An effective follow-up discussion should move from "Is this number borderline?" to "Does it change the next steps?" You can ask in this order:
Is this measurement reliable, and does the original image need review?
For my height, weight, and sex, is the reference approach used in the report appropriate?
Should this result be interpreted alone or together with other ultrasound indices?
Does it support a diagnosis, or can it only be recorded as uncertain or requiring observation?
Compared to previous examinations, is there a clinically significant change?
Will it change the timing of follow-up, additional tests, or referral?
If no immediate action is needed, what symptoms or changes should prompt earlier evaluation?
Is a review by a cardiac imaging specialist warranted, or should a repeat study be done at the same facility using consistent methods?
If the physician thinks no immediate intervention is needed, confirm the basis for follow-up rather than stopping follow-up on your own. If the physician recommends additional testing, ask what question the test will answer and how the result will affect subsequent decisions.
Which current chest discomfort, shortness of breath, or fainting cannot wait for report interpretation
Scheduling interpretation of an echo report cannot replace emergency evaluation. If you are having sudden or severe chest discomfort, significant shortness of breath, fainting, or rapidly worsening symptoms, contact local emergency services or go to an emergency department immediately; do not wait for a routine follow-up.
The following situations especially should not be managed at home by repeatedly reading the report:
Chest discomfort that is persistent, significantly worsening, or accompanied by sweating, nausea, extreme weakness, etc.
Shortness of breath that comes on suddenly, is significant at rest, or prevents lying flat
Fainting, altered consciousness, or near-fainting
Palpitations with significant dizziness, chest discomfort, or shortness of breath
Sudden neurological abnormalities such as one-sided weakness, slurred speech, or facial asymmetry
This list does not cover all emergencies and cannot be used to determine the specific cause. If unsure whether symptoms are urgent, contact a local healthcare professional for immediate guidance.
Check the boundary: A borderline value cannot by itself confirm normal or abnormal, nor decide treatment
"Borderline" usually suggests the result is near an interpretive boundary, but the boundary itself is not a diagnosis. Reference ranges may be affected by measurement method, units, body size correction, and applicable population. Reports may also have rounding, image quality limitations, or measurement variability.
Therefore, do not take the following actions based solely on a borderline number:
Self-diagnose the presence or absence of a heart condition
Start, stop, or adjust prescription medications on your own
Cancel physician-recommended follow-up because the result is "just off"
Disregard an official report because an online reference range differs
Directly compare your ultrasound values with others'
Infer from a single examination that the condition is worsening or improving
If the report interpretation is inconsistent with symptoms, prior examinations, or other physicians' opinions, you can request review of the original images, confirmation of measurement methods, or, if appropriate, a second opinion. The goal of re-evaluation is to clarify the basis, not to presuppose a particular conclusion.
Final action: Obtain a written follow-up summary that includes raw values and the basis for interpretation
Before ending the follow-up visit, ask for a written summary that includes at least:
The exact name of the borderline measurement, raw value, and units
Whether a body size or sex-specific reference approach was used
If corrected, the correction method and corrected result
The physician's assessment of image quality and measurement reliability
Comparability with previous examinations and whether the change is clinically significant
What can be confirmed now and what remains uncertain
Whether repeat testing, additional tests, or specialist review is needed
The rationale for the planned follow-up interval
Which symptoms should prompt earlier medical attention or emergency care
Before leaving, you can repeat in your own words: "My understanding is that this measurement currently means X, does not mean Y, and the next step is Z at W time." Ask the physician to correct any omissions to reduce overinterpretation of the word "borderline."
The most important thing is not to seek a simple normal or abnormal label for a number, but to confirm that the number has been interpreted using an appropriate method and cross-checked with symptoms, the complete ultrasound findings, and serial changes. Any diagnosis, follow-up frequency, or treatment decision should be made by a healthcare professional who knows the full clinical context.
Medical Health FAQ
1. When preparing for a weight loss consultation at the Heart Alliance, what information should patients with high blood pressure or coronary artery disease gather in advance?
Patients can compile recent weight fluctuations, daily eating and exercise patterns, and past weight loss attempts and challenges. During the consultation, tell the Heart Alliance physician what issues you want to prioritize, ask whether referral to a nutrition specialist is needed, and learn how to work with the physician to set personalized goals and follow-up plans. Do not blindly follow rapid weight loss methods found online, and do not take weight loss medications on your own.
2. If long-term fasting is required for religious or personal reasons, what should patients with high blood pressure or coronary artery disease discuss in advance with the Heart Alliance?
You should communicate in advance with your responsible physician at the Heart Alliance about the fasting duration, fluid restrictions, changes in daily routine, and current medications, and confirm whether fasting is appropriate for you and how to monitor your condition. Never change medication dosages or timing on your own. You can also consult Heart Alliance nutrition, pharmacy, or remote follow-up services; if sudden or severe discomfort occurs during fasting, stop the activity and contact local emergency services immediately.
3. When scheduling a hypertension or coronary artery disease appointment at the Heart Alliance, what should you do if the name on your ID does not match old medical records?
When scheduling, inform the Heart Alliance staff about the name discrepancy and ask what identity verification documents are acceptable, such as proof of former name or name change certificate. When submitting materials, indicate that both names refer to the same patient, and ask Heart Alliance to check existing records to prevent duplicate charts or incorrect linkage. If names are in different languages, provide the original spelling on the ID, and do not rewrite the name on old reports yourself.